
Introduction
Recent trials promote extending intravenous thrombolysis (IVT) window for acute ischemic stroke (AIS) beyond 4.5h in selected patients. We aimed to evaluate the extended-window (EWIVT) decision-making and outcomes in routine clinical practice.
Methods
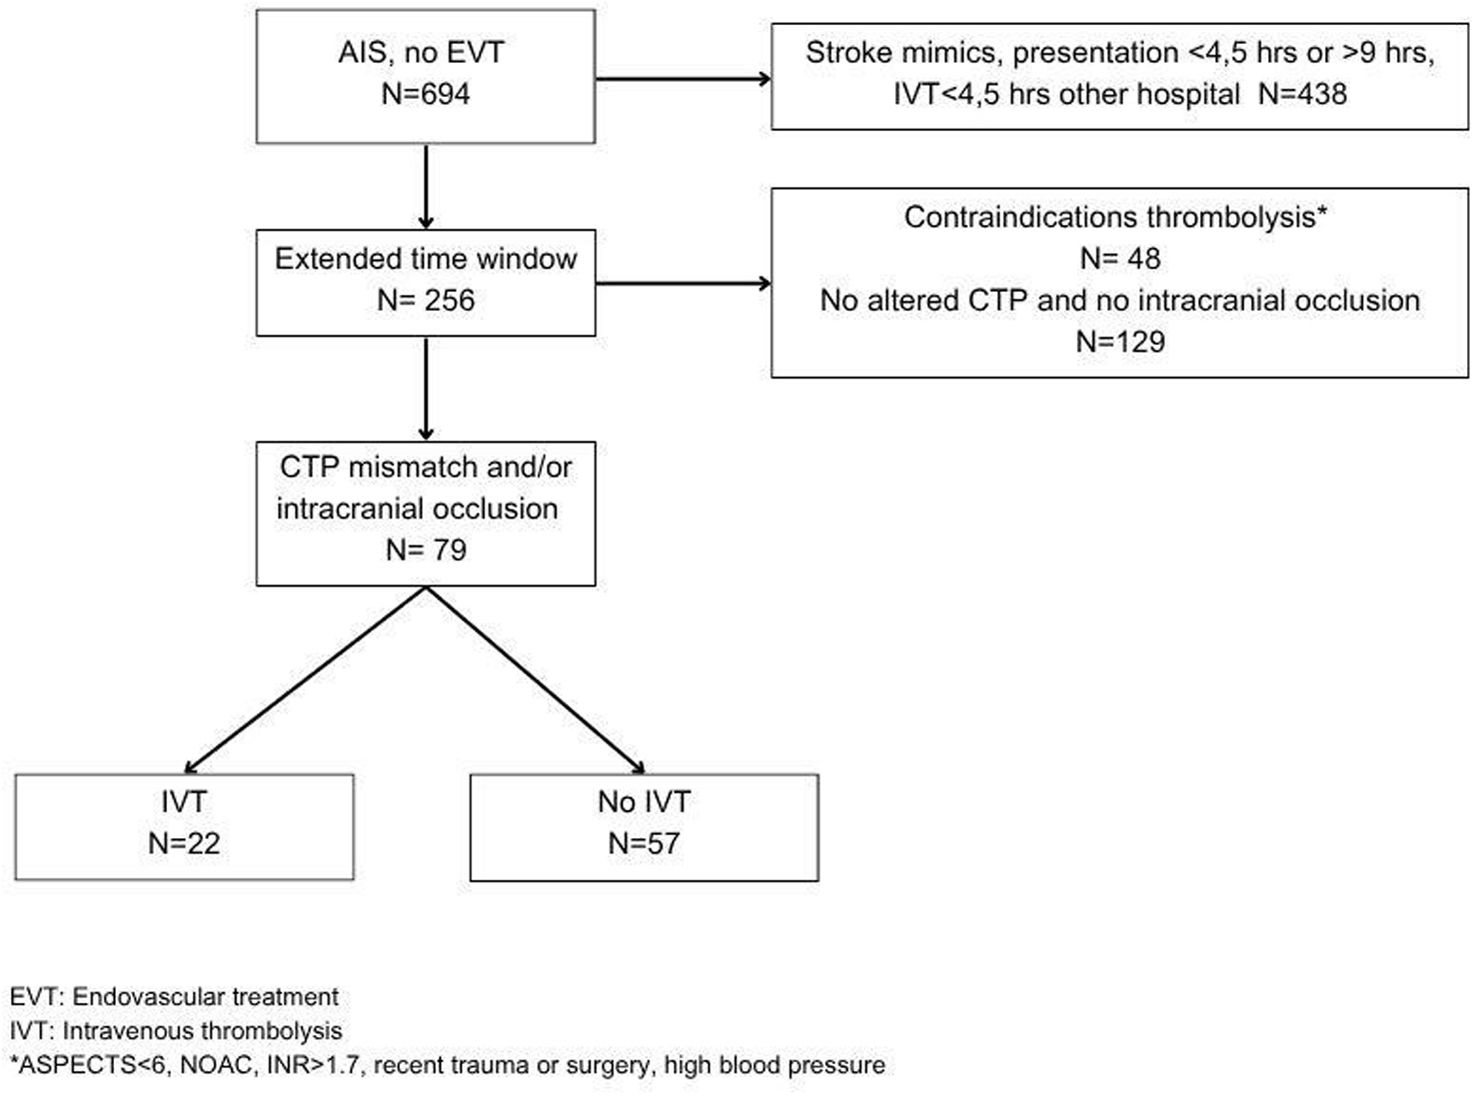
Retrospective analysis of a prospective uni-center mandatory stroke registry. AIS patients presenting within 4.5–9h from symptoms or wake-up strokes with mismatch on computed tomography perfusion (CTP) and/or intracranial occlusion without indication for thrombectomy were selected. We studied factors related to EWIVT treatment decision and compared efficacy (24h clinical improvement, 3-months modified Rankin Scale) and safety outcomes (symptomatic intracranial hemorrhage (SICH)).
Results
We included 79 patients (51.9% male, mean age 72.2y). Fifty-four (68.4%) had intracranial occlusion and 25(31.6%) CTP-mismatch. Twenty-two patients (27.8%) received EWIVT. EWIVT patients had similar baseline severity [NIHSS 4.5 (2.0–6.0) vs. 4.0 (2.0–6.5); p=0.596], higher ASPECTS [10.0 (10.0–10.0) vs. 10.0 (9.0–10.0); p=0.010] and more often presented with aphasia (63.6% vs. 24.6%; p=0.001). An adjusted logistic regression analysis showed that main predictors of EWIVT were higher ASPECTS and left hemisphere stroke. Clinical improvement at 24h was more frequent in the EWIVT group (77.3% vs. 36.8%; aOR 5.02 [95%CI 1.33–18.90]; p=0.017) and no patient experienced SICH, but a non-significant better functional outcome was found in the control group (aOR 0.19 [95% CI 0.03–1.19]; p=0.076).
Conclusions
Patients with a left hemisphere stroke and/or higher ASPECTS were more likely to be treated with EWIVT. EWIVT was safe and induced early clinical improvement, but did not lead to better functional outcome at 3 months.