Background
Management of patients with cutaneous melanoma and positive sentinel lymph node biopsy (SLNB) has shifted toward surveillance rather than complete lymph node dissection (CLND), because CLND has failed to demonstrate a survival benefit. However, evidence is still lacking as to whether patients with high-risk criteria might benefit from CLND.
Objectives
To evaluate the impact of CLND on melanoma-specific survival (MSS), overall survival (OS), nodal recurrence-free survival (NRFS), and local survival (LS) in a subgroup of high-risk patients.
Methods
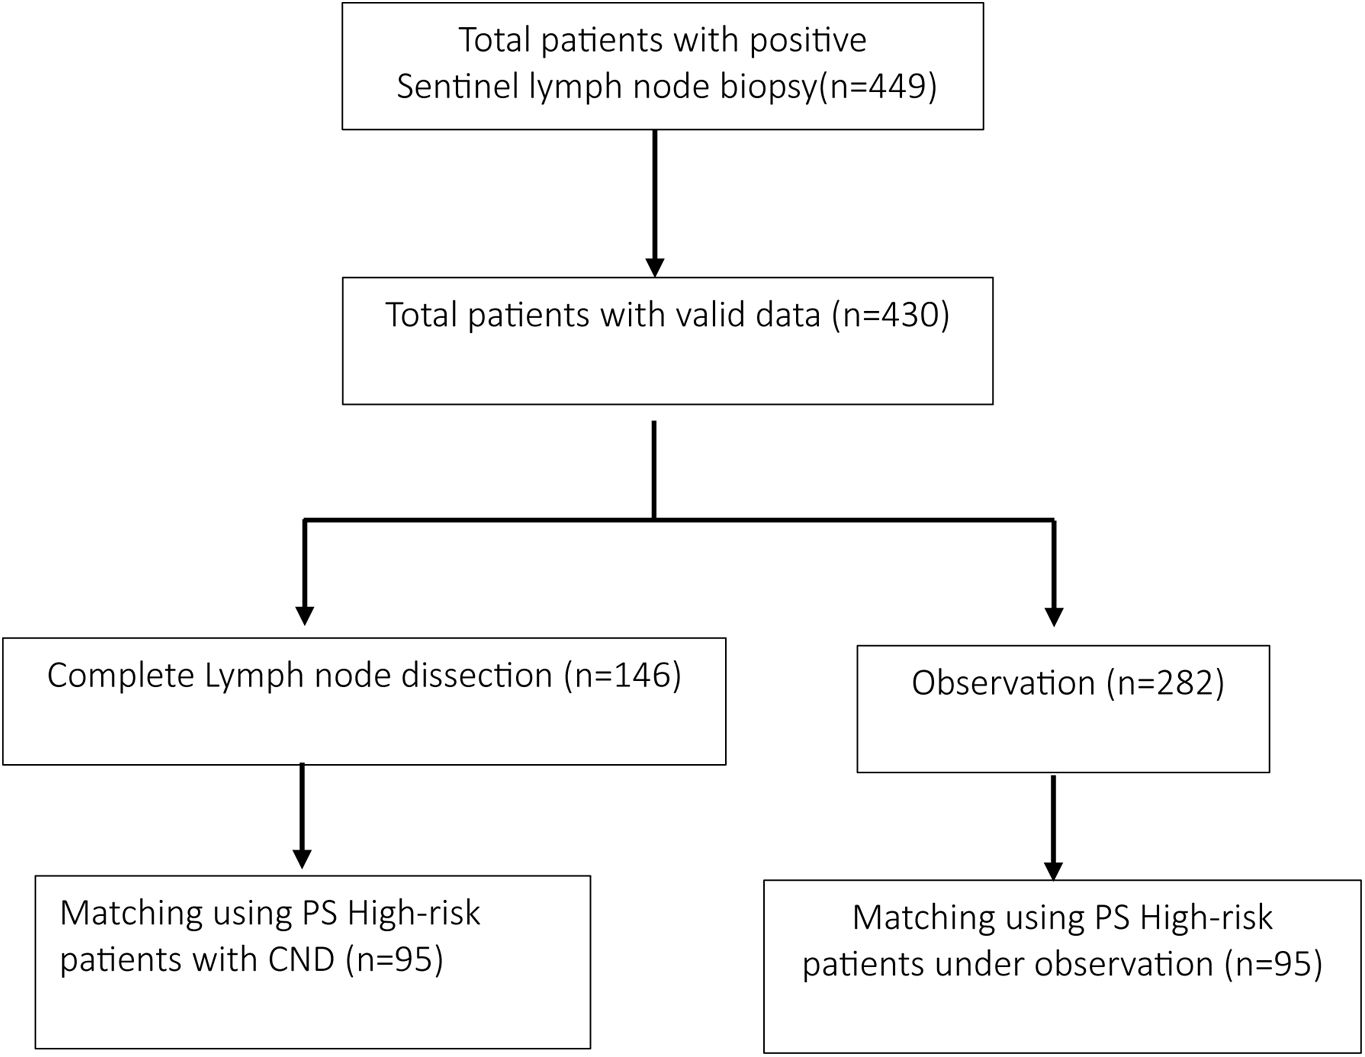
We designed a multicenter retrospective observational study, including patients with cutaneous melanoma diagnosed between 2017 and 2022 with positive SLNB and at least 1 high-risk feature: nodal metastasis >1mm, extracapsular extension (ECE), and/or involvement of >3 nodes. A propensity score-matched analysis comparing patients who underwent CLND with those who underwent surveillance was used to control for bias. Survival analysis was performed.
Results
A total of 190 patients (95 per group after matching) were analyzed. CLND showed no association with MSS, OS, NRFS, or LS. On multivariable analysis, lymphovascular invasion was associated with NRFS (HR, 2.5; 95%CI, 1.11–5.63; P=.02). MSS was associated with the presence of ulceration (HR, 4.18; 95%CI, 1.66–10.54; P=.002), extracapsular extension (HR, 3.1; 95%CI, 1.12–8.61; P=.03), and functional status [ECOG >0 (HR, 3.46; 95%CI, 1.46–8.24; P=.005)].
Conclusions
In patients with melanoma and positive high-risk SLNB, CLND does not appear to confer a significant survival benefit or prevent locoregional recurrence.